What the Anion Gap Calculator Calculates
An anion gap is a helpful measurement derived from an electrolyte panel that aids in evaluate acid-base balance and identify possible sources of metabolic acidosis. An anion gap calculator applies regular blood chemistry values to estimate the gap between typically measured cations and anions, especially serum sodium and serum chloride, with serum bicarbonate as part of the formula.
The outcome is reported in mEq/L, short for milliequivalents per liter. This unit represents charge concentration and is central to interpreting serum electrolytes in a way that extends beyond looking anion gap calculatoranion gap at each number separately. Because the body contains many unmeasured anions and cations, the anion gap acts as a diagnostic aid that can reveal patterns not obvious from the raw lab values alone.
Clinically, the anion gap helps narrow down the cause of an acid-base disorder. For example, a rising gap may indicate accumulation of acids, while a normal gap with low bicarbonate can point toward bicarbonate loss or a compensatory chloride increase. In practice, the calculator is most helpful when viewed together with the full clinical picture, including symptoms, medications, and other laboratory results.
Anion Gap Formula in mEq/L
The classic anion gap formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some clinicians also include potassium as part of the calculation:
Anion gap = sodium + potassium - (chloride + bicarbonate)
Each method state the result in milliequivalents per liter, but the sodium-only formula is used more often because potassium contributes only a small amount to the final value. An anion gap calculator may apply either version depending on its setup, but the key inputs remain the same: serum sodium, serum chloride, and serum bicarbonate, with optional potassium.
The reason this works plasma must remain electrically neutral. If the measured positive charge from sodium is far higher than the measured negative charge from chloride and bicarbonate, the difference indicates other ions not directly reported on the standard panel. That is why the anion gap is so helpful in evaluating metabolic acidosis and distinguishing high anion gap acidosis from normal anion gap acidosis.
For daily use, the formula is simple, but its interpretation is less straightforward. A bicarbonate decrease may occur in various acid-base conditions, and the corresponding shift in chloride or other ions can change the calculated result. This makes the formula a first step for clinical interpretation, not the final answer.
How to Operate the Anion Gap Calculator
In order to determine the anion gap with an anion gap calculator, provide the values from the patient’s chemistry panel. The primary calculator inputs are:
- Na value Chloride level HCO3 value Potassium, provided that the calculator includes it
Once the values are added, the calculator returns the anion gap in mEq/L. It is especially helpful when checking an electrolyte report quickly, such as when evaluating a patient with possible acid-base acidosis, unexplained illness, or a suspected electrolyte disturbance.
For the best result, use values from the same specimen and the same lab draw whenever possible. Combining values from different time points can distort the result and weaken the value of the calculation. Furthermore, be sure the units match the expected format. Anion Gap Calculator assumes the lab values are reported in conventional chemistry units that can be interpreted as milliequivalents per liter for the purpose of the formula.
After the result is displayed, compare it with the lab’s expected range. The calculator may flag a low, normal, or high result, but the meaning depends on the full context, including albumin, acid-base status, and whether other abnormalities are present.
Standard Anion Gap Range and Reference Values
The usual range for the anion gap is influenced by the lab and the method used. A common normal interval may be around 8 to 12 mEq/L when potassium is excluded, though some laboratories report slightly different values. As a result, it is important to use the specific lab’s reference interval rather than relying on a single universal cutoff.
Method differences matter. The same patient sample may produce different results depending on the analyzer, the measurement technique, and the lab’s calibration. This is one reason laboratory variation can affect how an anion gap is interpreted. A value that appears borderline in one setting may be completely expected in another.
Albumin also affects the expected range. Since albumin is a major unmeasured anion, lower albumin levels tend to lower the anion gap. That means a “normal” result may not always be reassuring if low albumin is present. In such cases, the apparent normal value can hide an elevated gap after adjustment.
As a result, the raw number should be viewed as one piece of the larger acid-base puzzle. A gap within the reference interval does not automatically rule out disease, and a slightly elevated value does not always mean a major pathologic process is present. The clinical context and the rest of the blood chemistry are essential.
Elevated Anion Gap Causes
A increased anion gap is commonly associated with buildup of acids in acidosis. This pattern indicates that unmeasured anions are rising, typically because acid is being added to anion gap the body or because acid clearance is impaired. A common approach is to think in terms of high anion gap acidosis and then identify the underlying source.
Some of the most common causes include:
- Lactic acidosis, which may happen when tissues are underperfused or oxygen delivery is impaired Ketoacidosis, including diabetic, alcoholic, or starvation-related forms Renal failure, where the kidneys cannot remove acid effectively
Lactic acidosis adds to acid load and can rapidly raise the anion gap. Ketoacidosis causes the buildup of ketone bodies, which are unmeasured anions. In renal failure, the body holds onto acids that would normally be excreted, steadily shifting the acid-base balance toward a higher gap.
Other causes may also be involved, including toxin exposures, severe illness, or marked disruption of metabolism. The key point is that a high gap often suggests that the body has gained acids or lost the ability to clear them. That makes the result useful as an early clue, but not as a final diagnosis.
Standard Anion Gap Metabolic Acidosis Causes
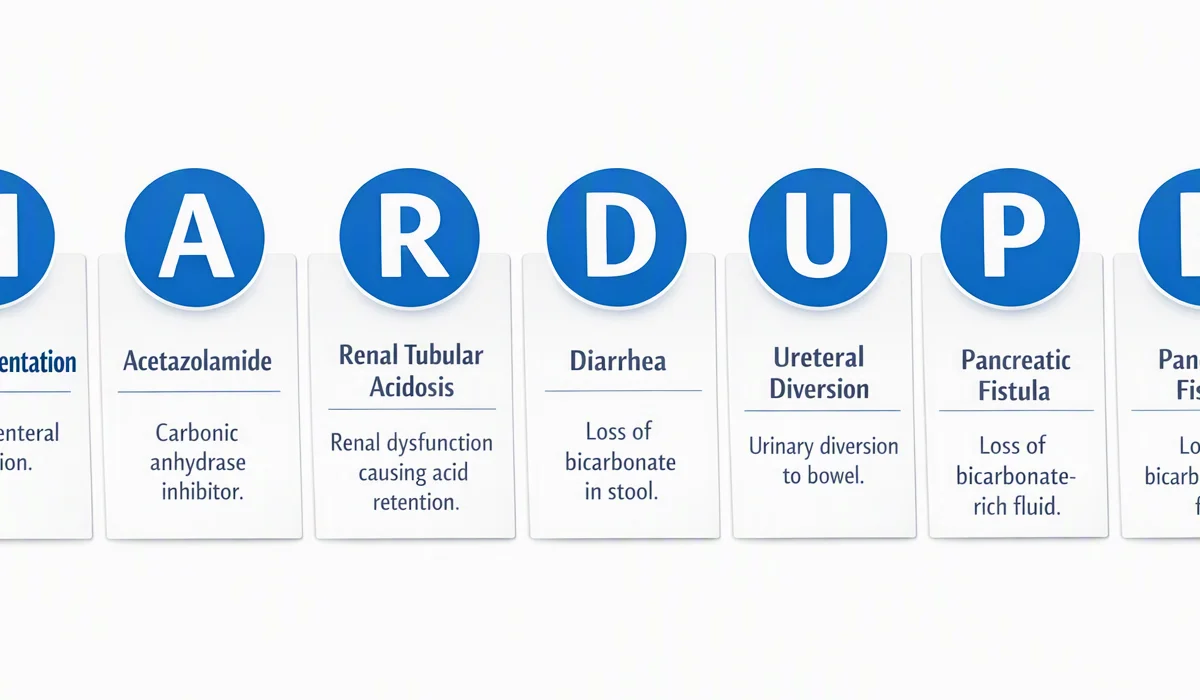
Not all acidosis presents with a raised gap. A normal anion gap pattern, sometimes called normal anion gap acidosis, usually reflects reduction of bicarbonate rather than buildup of unmeasured acids. This pattern is frequently labeled as hyperchloremic metabolic acidosis because the fall in bicarbonate is paired with a slight rise in chloride.
Common causes include diarrhea, renal tubular acidosis, and other forms of gastrointestinal loss. In diarrhea, bicarbonate is removed through the digestive tract. The body may adapt by retaining chloride, creating the classic hyperchloremic pattern. In renal tubular acidosis, the kidneys fail to acidify the urine properly or cannot reclaim bicarbonate adequately, again resulting in a normal gap acidosis.
This pattern is clinically important because the lab values can look deceptively ordinary except for the bicarbonate and chloride changes. A patient may have low bicarbonate, a normal anion gap, and significant symptoms. Recognizing the pattern helps distinguish bicarbonate loss from acid accumulation.
In practice, the presence of a normal gap does not mean the patient is fine. It merely indicates a different mechanism. That is why reviewing the full electrolyte panel and the clinical story is essential.
Albumin Correction and Adjusted Anion Gap
Albumin correction is an important step when hypoalbuminemia is present. Since serum albumin plays a major role to the unmeasured anions in blood, a low albumin level can make the measured anion gap look artificially low or normal. In these situations, the corrected anion gap provides a better reflection of the patient’s acid-base state.
A common correction formula includes a set amount to the measured gap for every decrease in albumin below normal. Different institutions may use slightly different adjustment methods, but the concept is the same: lower albumin means the expected baseline anion gap should be lower, so the measured result needs to be adjusted upward to avoid missing hidden acidosis.
This becomes especially important when the clinical picture suggests acid accumulation but the raw anion gap is not strikingly elevated. For example, a patient with low albumin may still have clinically important metabolic acidosis even if the uncorrected number seems only mildly abnormal. In such cases, the corrected anion gap can reveal a problem that would otherwise be overlooked.
Using albumin correction does not replace the rest of the workup. It simply improves the interpretation of the anion gap in patients with altered protein status, including those with chronic illness, inflammation, liver disease, or malnutrition.
How to Understand the Result
Interpreting the value requires more than labeling it as high. Good clinical interpretation opens by asking whether the result matches the patient’s symptoms, the rest of the laboratory values, and the likely acid-base disorder. A slightly elevated gap may be significant in one context and less relevant in another.
If the anion gap is elevated, think about metabolic acidosis from acid accumulation. If the gap is normal but bicarbonate is low, consider normal anion gap acidosis, chloride-driven changes, or bicarbonate loss. If the result is abnormally normal in a sick patient, consider albumin correction, a mixed picture, or a timing issue with the blood draw.
It also helps to check the full electrolyte panel for clues such as:
- Decreased bicarbonate with rising chloride Abrupt sodium shifts Potassium abnormalities Indicators of electrolyte imbalance across multiple values
A useful way to think about the result is as a pattern recognition aid. The anion gap does not diagnose the cause by itself, but it helps distinguish likely mechanisms and supports the next step in evaluation. That is why it remains a valuable part of blood chemistry review in many settings.
Key Limitations of an Anion Gap Calculator
Even a well-designed anion gap calculator has limitations. One major issue is measurement error. Small differences in sodium, chloride, or bicarbonate can noticeably change the final result, especially when the number is near the cutoff between normal and abnormal. Because of this, slight changes should be interpreted carefully.
The lab method used to measure electrolytes can also affect the calculation. Different analyzers may produce slightly different sodium or chloride values, which shifts the anion gap. That is one reason the reference interval should always come from the same laboratory that produced the patient’s results.
One more drawback is that the equation only covers a portion of blood charge balance. Many key ions are not directly measured. As a result, unmeasured ions such as certain acids or toxins can affect the gap without being clear from the standard panel. Likewise, a patient may have a seemingly normal result while still having a important mixed acid-base disorders picture.
A mixed disorder can obscure the expected pattern. For example, a raised anion gap acidosis might be present with a metabolic alkalosis or a normal gap acidosis, producing a unclear or misleading number. This is why the anion gap calculator should be used as part of a broader assessment rather than as a stand-alone verdict.
FAQ
What does an anion gap calculator do?
An anion gap calculator is used to calculate the anion gap from routine blood chemistry values and help interpret acid-base balance. It is most helpful for evaluating metabolic acidosis, spotting a possible high anion gap, and recognizing when a normal anion gap pattern suggests bicarbonate loss or chloride-related changes.
What is the formula for anion gap in mEq/L?
To calculate anion gap in mEq/L, follow the formula: serum sodium minus the sum of serum chloride and serum bicarbonate. Some versions also include potassium. The result is expressed in milliequivalents per liter, which reflects the balance of measured ions in the blood.
What is a normal anion gap range?
The normal range depends on the lab and its reference range. A common reference interval is around 8 to 12 mEq/L when potassium is not included, but lab variation can move that value. Always interpret the result using the laboratory’s own standards.
Why do you correct the anion gap for albumin?
You adjust the anion gap for albumin because serum albumin is a major unmeasured anion. In hypoalbuminemia, the measured gap can seem falsely low or normal. Using a correction formula gives a more accurate corrected anion gap and helps avoid missing hidden acidosis.
What does a high anion gap mean?
A high anion gap usually means there are excess unmeasured acids in the blood, which points toward metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should always be interpreted in combination with symptoms, the full electrolyte panel, and other laboratory values.