An Anion Gap Calculator enables doctors, students, and knowledgeable readers calculate and analyze the anion gap from common serum electrolytes. The value is a helpful screening tool for acid-base imbalances, especially when evaluating metabolic acidosis. Because albumin is a key contributor to unmeasured negative charge in the blood, the raw anion gap can be deceptive in hypoalbuminemia. That is why an albumin-corrected anion gap is often better for clinical use than the measured value alone.
This article outlines what the anion gap measures, how the anion gap formula is applied, how to make the albumin adjustment, and how to use the result for clinical interpretation. The goal is to move from a measured number to a more accurate view of acid-base status and the underlying cause of an abnormal result.
What exactly the anion gap shows
The anion gap is a calculated result based on serum electrolytes. It compares the main measured positive ions and anions in the blood, most commonly sodium, chloride, and bicarbonate. The calculation reflects the difference between positively charged particles that are measured and measured negatively charged particles, while also indirectly estimating unmeasured ions.
In simple terms, the anion gap can reveal whether there are additional acids or other unmeasured substances in the bloodstream. That makes it especially useful when evaluating acid-base disorders and determining whether a patient has metabolic acidosis. A normal result does not always eliminate pathology, but an abnormal result often points toward a specific diagnostic path.
The standard calculation is based on standard chemistry values from an electrolyte panel. Because sodium is typically the main measured cation and chloride plus bicarbonate are the main measured anions, the difference between them offers a clinically meaningful clue about the balance of electrolytes and the presence of unmeasured anions.
Commonly, the anion gap is used as a diagnostic aid rather than a stand-alone diagnosis. The number must be interpreted in combination with symptoms, blood gas data, and the broader laboratory picture.
Why albumin changes the anion gap
Albumin serves as the primary unmeasured anion in plasma. Its protein charge contributes significantly to the normal anion gap. When albumin is low, fewer negatively charged proteins are present in the blood, so the measured anion gap can appear below expectations even when acid-base pathology is present.
This matters because hypoalbuminemia can conceal a true increase in unmeasured acids. A patient may have substantial metabolic derangement, but the measured gap looks only a little increased or even normal. In https://anion-gap-calculation.com/reference/glossary.html that setting, albumin correction improves clinical significance and makes the result more precise for clinical interpretation.
Albumin is also essential for maintaining acid-base balance. Since it carries negative charge, changes in albumin concentration alter the difference between measured cations and anions. If albumin drops, the expected range of the anion gap shifts downward. This is why a raw value should not be considered in isolation when serum albumin is abnormal.
In practical terms, low albumin can obscure a higher-than-expected acid burden. Correcting the anion gap helps clinicians identify an abnormal result that might otherwise be dismissed as normal.
How to compute the albumin-corrected anion gap
The anion gap formula most often used is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Once the value is calculated, the corrected anion gap can be worked out by accounting for albumin. A common albumin adjustment applies about 2.5 mEq/L to the measured anion gap for every 1 g/dL reduction in albumin below 4.0 g/dL. In other words, lower albumin means the corrected value rises to better represent the true acid burden.
A practical correction can be expressed as follows:
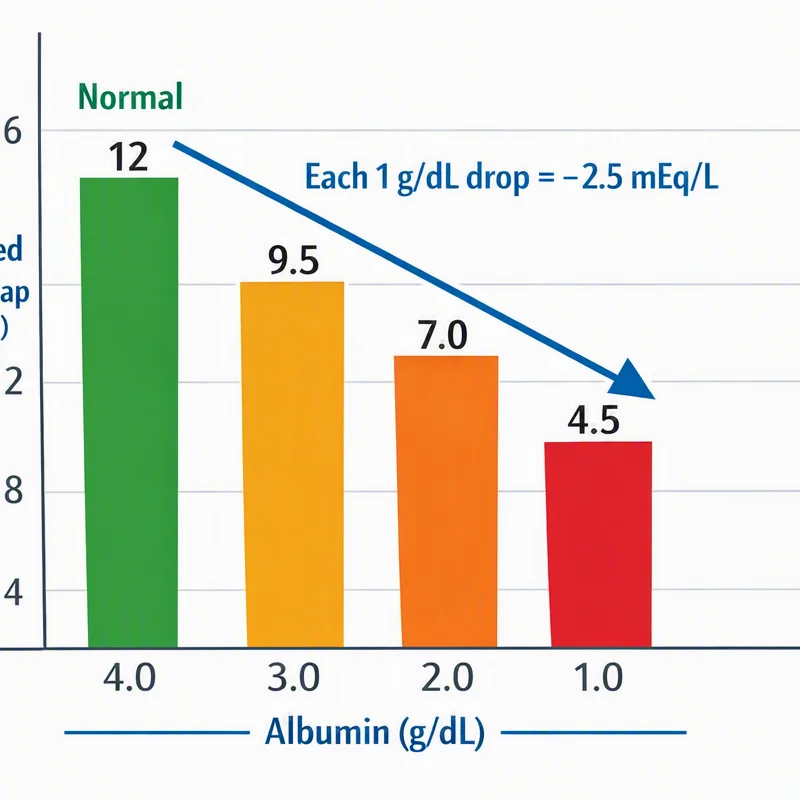
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - albumin in g/dL)
This adjustment offers a more realistic expected range for patients with low albumin. It is not a perfect law, but it is a well-accepted clinical estimate that improves interpretation. The goal is to contrast the measured value with a corrected value rather than rely on the raw number alone.
The concept of normal range can vary by laboratory because of differences in analyzer methods and reference intervals. Even so, albumin correction helps normalize evaluation when the albumin level is clearly below normal. That is especially useful in hospitalized patients, where the raw anion gap may miss the true degree of metabolic disturbance.
Remember that the albumin-corrected anion gap is a calculated estimate, not a direct measurement. It should assist, not replace, the overall evaluation.
How to operate an Anion Gap Calculator
An Anion Gap Calculator is a convenient way to calculate both the measured and adjusted gap from standard lab values. Most calculators request sodium, chloride, bicarbonate, and albumin. Some tools also allow the user to input the local reference range so the result can be compared against the lab’s own standards.
A basic step-by-step calculation usually takes this sequence:
- Enter the sodium value from the serum labs. Add the chloride value. Input the bicarbonate value. Enter the albumin value if correction is needed. Work out the measured anion gap. Use the albumin adjustment to estimate the corrected anion gap. Review the result with the lab’s reference range and the clinical picture.
For example, if sodium is 140, chloride is 104, bicarbonate is 20, and albumin is 2.0 g/dL, the measured anion gap is 16. The albumin-corrected anion gap is above the measured value than the measured value because hypoalbuminemia lowers the uncorrected result. In that case, the calculator helps reveal a greater acid-base abnormality than the raw number suggests.
That is why calculator use is more than a convenience. It serves as a screening tool that helps clinicians quickly identify whether the measured value matches the expected range. If not, the discrepancy can direct further evaluation.

The best use of the calculator is stepwise: work out the gap, correct it when albumin is low, and then review the result within the full acid-base context. If needed, confirm the findings with blood gas analysis, lactate, ketones, renal studies, or toxicology testing.
Reading high, normal, and low anion gap results
A raised anion gap suggests an increase of unaccounted for anions, often due to acids. This pattern is classically associated with high anion gap metabolic acidosis. When the gap is elevated, the clinician should assess whether the result reflects elevated lactic acid, ketone build-up, kidney dysfunction, or toxic ingestion.
A normal anion gap does not always mean there is no metabolic problem. It can occur in normal anion gap metabolic acidosis, where bicarbonate is lost and chloride rises proportionally, keeping the difference relatively stable. This pattern is often called chloride-responsive metabolic acidosis.
A low anion gap is less common but can be meaningful. It may result from hypoalbuminemia, lab artifact, or marked rises in positively charged proteins or other substances. Because low values are often overlooked, they deserve close attention, especially if the number does not fit the rest of the clinical picture.
When evaluating metabolic acidosis, the anion gap is one piece of the puzzle. It helps sort acid-base disorders into broad categories and points toward an underlying cause. However, the measured value alone cannot confirm the diagnosis without clinical interpretation and related laboratory data.
Typical causes of unusual anion gap values
Many conditions frequently produce a increased anion gap metabolic acidosis. Some of the key causes are lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. All of these raises unmeasured acids or acid precursors in the bloodstream.
Lactic acidosis develops when lactate accumulates, commonly in settings of tissue hypoperfusion, severe infection, shock, seizures, or hypoxia. As lactate is an unmeasured anion, the anion gap rises as bicarbonate is consumed neutralizing the acid load.
Ketoacidosis occurs when ketone bodies build up, as seen in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Such ketones also increase the gap and lower bicarbonate.
Renal failure can elevate the gap because impaired kidney function reduces acid excretion and allows sulfate, phosphate, and other acids to accumulate. It is a common and major cause of persistent metabolic acidosis.
Toxic alcohols such as methanol and ethylene glycol can also produce a high gap. They are dangerous because they may initially present with nonspecific symptoms, while acid-base testing reveals the metabolic disturbance. In certain cases, the anion gap may help trigger urgent evaluation even before the toxic substance is confirmed.
Further causes of abnormal results include changes in serum proteins, shifts in measured electrolytes, and laboratory artifacts. That is why the anion gap should be viewed as a clue, not a final answer.
When albumin correction matters most
Correcting for albumin is especially helpful when the patient has situations associated with reduced albumin levels. This covers critical illness, malnutrition, cirrhosis, and nephrotic syndrome. In these settings, the raw anion gap may downplay the true acid load.
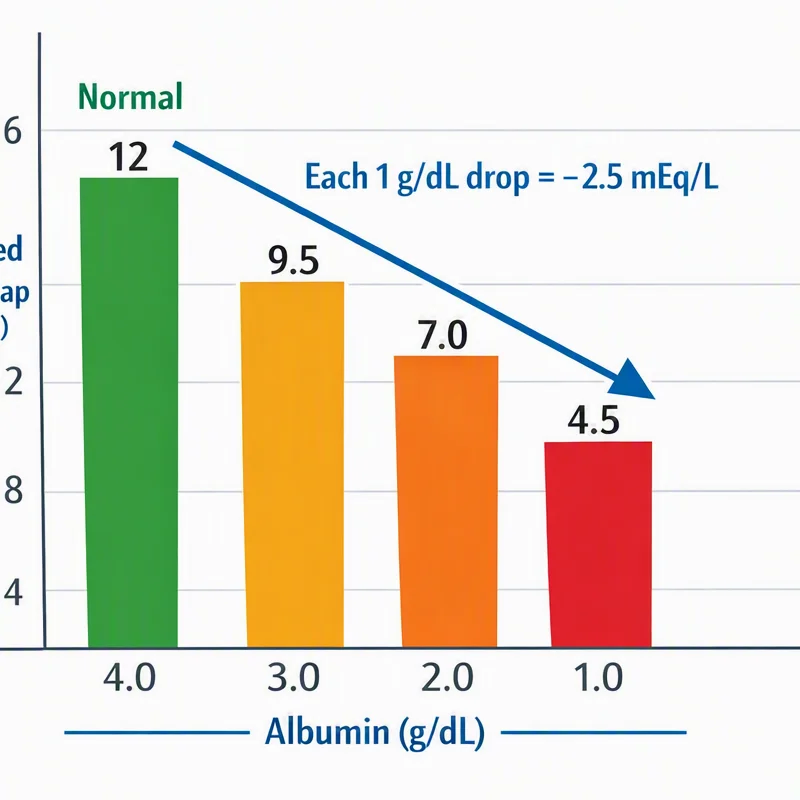
In critical illness, inflammation, fluid shifts, and poor nutrition often reduce albumin. A patient may appear to have a modest anion gap when the corrected value would show a more significant abnormality. That makes adjustment particularly important for prompt identification of acid-base disorders.
Malnutrition can lower albumin over time, changing the interpretation of routine serum labs. The same is true in cirrhosis, where reduced hepatic synthetic function contributes to hypoalbuminemia. In nephrotic syndrome, albumin is lost through the kidneys, again lowering the measured baseline gap.
In these populations, the albumin-corrected anion gap is not mere extra detail; it is a more accurate estimate of the actual acid-base status. That can change whether a result is interpreted as slightly abnormal or clearly abnormal.
Limitations of the anion gap calculation
Although the anion gap is helpful, it has notable limitations. One issue is lab variation. Different instruments and assay methods can yield slightly different values, which affects the reference range. This means a result that is normal in one lab may look borderline in another.
Measurement error is another concern. Small inaccuracies in sodium, chloride, or bicarbonate can alter the calculated gap, since the formula depends on subtracting similar numbers. Even a modest analytic difference can shift the result enough to change interpretation.
Albumin correction itself is an indirect adjustment, not a direct test of acid burden. The correction factor is practical, but it does not replace a full evaluation. Other factors, such as unusual proteins, unmeasured cations, or severe electrolyte disturbances, can make harder interpretation.
Above all, the anion gap must always be interpreted in clinical context. Signs and symptoms, vital signs, patient history, medicines, kidney health, lactate, ketone bodies, and blood gas findings all are important. A derived value without context can be misleading, especially if the measured result is just a little abnormal.
For this reason, the anion gap is best used as part of a broader assessment. It can indicate a probable condition, but the final clinical interpretation is based on the overall situation.
Common questions
What does mean anion gap calculator with albumin adjustment?
An anion gap calculator with albumin adjustment is a tool that computes the anion gap value from sodium, chloride, and bicarbonate, then adjusts the result for low albumin. It helps improve clinical interpretation by giving a more accurate estimate of acid-base status when hypoalbuminemia is present.
Why does low albumin lower the anion gap?
Reduced albumin reduces the anion gap because albumin holds significant protein charge and acts as an unaccounted anion. When albumin decreases, the measured gap decreases even if there is still an underlying acid-base disorder. That is why albumin correction is essential for precise assessment.
How do you calculate the corrected anion gap?
First determine the basic anion gap formula: Na minus chloride plus bicarbonate. Then make an albumin correction, commonly increasing by 2.5 mEq/L for each 1 g/dL albumin less than 4.0 g/dL. The result is the albumin-corrected anion gap.
What is a normal anion gap after albumin correction?
The usual range depends on the laboratory’s reference range, because different assays generate slightly different values. After albumin correction, the result should be compared with the lab’s normal range and the overall clinical picture. A “normal” value still needs interpretation if symptoms or other labs suggest metabolic disease.
When should anion gap results be interpreted with clinical context?
Anion gap results should consistently be interpreted with clinical context, especially when the patient has acidosis, hypoalbuminemia, renal impairment, shock, or possible toxin exposure. The number is a practical screening tool, but diagnosis requires confirmation using the full evaluation, including serum labs, patient symptoms, and other tests.